

Chiropractic care, delivered as part of a broader conservative plan, is a reasonable and noninvasive option for many people with sciatica when no red flags are present. A recent retrospective cohort study found that patients who first received chiropractic spinal manipulation had a lower incidence of opioid-related adverse events over the following year. Your first step is a clinical assessment to screen for red flags and build a treatment plan suited to your case.
TL;DR:
- Chiropractic care is most effective for sciatica caused by mechanical issues in the spine or piriformis muscle, with improvements often seen in four to eight visits.
- Patients who start with chiropractic spinal manipulation tend to have a lower risk of opioid prescriptions and adverse events over the following year compared to usual care.
- Red flags such as numbness in the saddle area, bowel or bladder dysfunction, and progressive leg weakness require urgent medical assessment and imaging.
- Treatment success depends on combining joint and soft-tissue techniques with exercise and posture education, not relying on manipulation alone.
- Home exercises like piriformis and hamstring stretches, nerve glides, and activity pacing support recovery and help prevent setbacks.
Sciatica describes pain that radiates along the sciatic nerve, usually from the lower back through the buttock and down the leg. In many cases, the irritation starts with a mechanical problem: a restricted joint in the lumbar spine, a bulging or herniated disc pressing near a nerve root, or tight muscles compressing the nerve along its path. Chiropractic care targets these mechanical contributors directly.
Spinal manipulation and mobilization aim to restore normal motion to stiff or restricted joints, which can reduce the pressure and irritation affecting nearby nerve roots. When a disc is involved, gentler techniques are often used to avoid aggravating the area while still encouraging better movement patterns around it.
Soft tissue also plays a role. The piriformis muscle, which sits close to the sciatic nerve, can tighten and press on the nerve, a pattern sometimes called piriformis syndrome. Manual release techniques address this muscle directly, which can ease the entrapment and reduce referred leg pain.
Because sciatica rarely has a single cause, chiropractors typically build a plan around more than manipulation alone:
This combination reflects how most current guidance frames the treatment: manual therapy works best as one part of a package that also includes movement and self-management, not as a stand-alone fix.
Once your chiropractor has assessed your spine, muscles, and nerve function, treatment usually draws from a small set of well-established techniques matched to your presentation.
High-velocity, low-amplitude (HVLA) spinal manipulation is the classic adjustment: a quick, controlled thrust to a joint that has lost normal motion. Mobilization applies similar goals with slower, gentler pressure, and instrument-assisted techniques such as the Activator offer a lower-force alternative for patients who prefer less direct manipulation or have contraindications to HVLA work.
Soft-tissue methods often run alongside spinal treatment. Active Release Technique and Graston Technique target adhesions and tension in muscles like the piriformis, while therapeutic massage can ease trigger points contributing to referred pain. These approaches complement joint work rather than replace it.
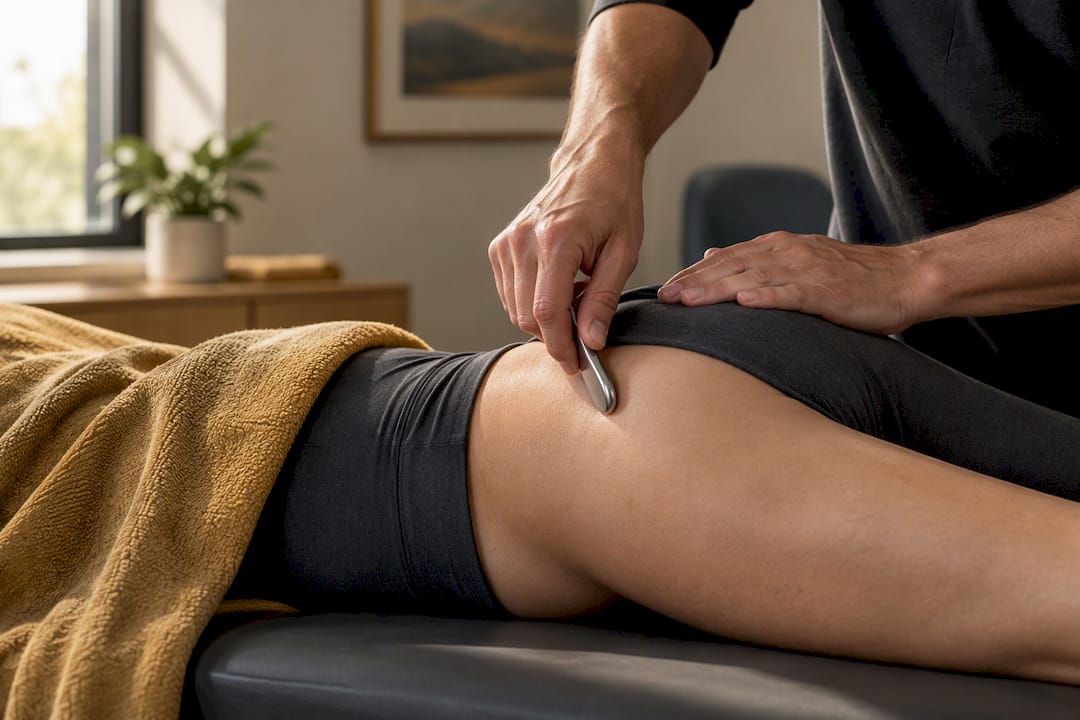
Some clinics add adjunctive therapies, including spinal decompression, laser therapy, and shockwave therapy, intended to support tissue healing and reduce pressure on affected structures. These are generally used as supporting tools alongside manual therapy rather than as primary treatments on their own.
Between visits, home elements matter:
Pro Tip: Ask your chiropractor to demonstrate any home exercise in the office first, so you know exactly what “correct” feels like before doing it alone.
Clinical guidance from multiple sources converges on a similar message: manual therapy has a place in treating sciatica, but only as part of a broader plan. NICE guidance recommends considering manual therapy, including spinal manipulation, mobilization, or soft tissue techniques, only as part of a package that also includes exercise, and advises against routine opioid use for sciatica. Canadian primary-care guidance similarly supports referral to a spinal care specialist, including chiropractors, for disabling back or leg pain, and treats imaging as something reserved for red flags or cases where it would change management.
The strongest recent evidence on outcomes comes from a 2025 retrospective cohort study in PLOS One, which followed adults with sciatica and compared those who initially received chiropractic spinal manipulation against matched patients receiving usual medical care.
After propensity matching, patients who started with chiropractic spinal manipulation had substantially lower rates of opioid-related adverse events and oral opioid prescriptions compared to usual care, indicating a significantly reduced relative risk, according to the PLOS One study. In plain terms, patients who started with chiropractic care were considerably less likely to end up on opioids or experience an opioid-related complication over the following year.
A few caveats matter here:
Taken together, the guidance and the outcomes data support chiropractic care as a legitimate first-line option for appropriate candidates, with realistic expectations about what it can and cannot do alone.
Most people with sciatica caused by mechanical joint restriction, mild-to-moderate disc irritation, or piriformis-related nerve compression are reasonable candidates for chiropractic care. Symptoms that are controllable, without progressive weakness or signs of a broader medical problem, generally respond well to a conservative approach.
Certain symptoms, however, call for urgent medical evaluation rather than chiropractic care. Watch for:
A thorough chiropractic assessment includes screening for these signs before any hands-on treatment begins. When a red flag is present, or when symptoms do not fit a straightforward mechanical pattern, the appropriate step is imaging or referral, consistent with guidance that reserves imaging for cases where red flags exist or the result would genuinely change the treatment plan.
A typical course starts with a detailed assessment covering your history, movement patterns, and neurological screening, followed by a short course of hands-on care. Many patients with mechanical sciatica notice meaningful improvement within four to eight visits, with an early sense of direction often clear within the first two weeks.
Progress is usually tracked functionally rather than by pain scores alone:
Home exercise adherence between visits tends to influence how quickly these markers shift. If you are not seeing progress after several weeks of consistent care, or if new or worsening neurological signs appear, a good chiropractor will reassess and consider whether referral or imaging is warranted rather than continuing the same plan indefinitely.
Between visits, a few simple habits can support your recovery without risking setbacks.
Stop any exercise immediately if it increases radiating pain down the leg or triggers new numbness or weakness, and contact your chiropractor before continuing.
Pro Tip: If a stretch feels better one day and worse the next, back off the intensity rather than pushing through, sciatic nerve irritation often responds poorly to force.
Chiropractic care for sciatica carries a low rate of serious complications when patients are properly screened. Guideline summaries from the Canadian Chiropractic Guideline Initiative support multimodal conservative care, combining manipulation with exercise, as first-line treatment for many cases, while noting that evidence quality varies across techniques and conditions.
Certain conditions call for caution or alternative approaches instead of standard manipulation:
When manipulation is not appropriate, chiropractors trained in red flag screening typically shift to low-force mobilization, soft-tissue techniques, or co-management with a physician. Informed consent, including a clear discussion of risks and expected sensations, and ongoing monitoring during treatment are standard parts of safe care.
Shephard Health builds sciatica care plans around a comprehensive biomechanical assessment rather than a one-size-fits-all adjustment. The clinic’s approach typically draws on several tools depending on what the assessment finds:
These modalities are typically combined into an individualized plan built around restoring function and getting patients back to normal activity, not just reducing pain in the moment.
Ask your chiropractor directly what your imaging thresholds are, what your expected timeline looks like, and what your home program will involve before your first adjustment. Good care is a shared process: track functional wins, like walking farther or sleeping through the night, rather than fixating on pain scores alone.
Set a checkpoint for yourself, four to eight visits is a reasonable window, and revisit the plan with your provider if progress stalls. If you are ready to start that conversation, a clinic assessment is the natural next step.
— Deane
If mechanical sciatica is limiting your walking, sitting, or sleep, Shephard Health offers a direct path forward without a long wait for a first appointment. Availability for prompt biomechanical assessments and support for insurance billing aim to facilitate access to treatment.
Depending on what that assessment finds, your plan might include Active Release Technique for soft-tissue involvement, spinal decompression for disc-related pressure, or shockwave therapy and laser therapy as supporting care. Your first visit will cover a full history, movement and neurological screening, and a plan built around your specific pattern of symptoms. Visit the Shephard Health services page to see the full range of options and book an assessment.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Chiropractic care, delivered alongside exercise and education, is considered a reasonable option for many people with mechanical sciatica. A 2025 cohort study found that patients who started with chiropractic spinal manipulation had a substantially lower incidence of opioid-related adverse drug events over the following year compared to those receiving usual medical care.
There is no single best treatment for every case. Guidance generally supports combining manual therapy, such as chiropractic manipulation or mobilization, with structured exercise and education, reserving stronger interventions for cases that do not improve or that show red flag symptoms.
Avoid prolonged sitting, forcing painful stretches, or ignoring new numbness, weakness, or bowel and bladder changes. These red flag symptoms warrant prompt medical evaluation rather than continued self-treatment or chiropractic care alone.
Release typically involves a combination of soft-tissue techniques, such as Active Release Technique or targeted massage for the piriformis muscle, alongside joint mobilization and nerve-gliding exercises. A chiropractor can assess which structures are involved and choose techniques suited to your specific pattern of nerve irritation.
Same Day Appointments Available
We Direct Bill!