

A tension headache feels like a tight band squeezing both sides of your head, mild to moderate, and rarely brings nausea. A migraine tends to hit one side, throb rather than press, and often drags nausea, light sensitivity, or an aura along with it. If your pain is mild and manageable, home care usually works; if it’s severe, one-sided, or paired with nausea and light sensitivity, treat it as a migraine and talk to your doctor about targeted options.
TL;DR:
- Most tension headaches are bilateral, pressing, and mild to moderate, with little to no nausea, and do not worsen with physical activity.
- Migraines are typically one-sided, throbbing, and can be severe, often accompanied by nausea, light sensitivity, and worsening with exertion.
- Common triggers for tension headaches include poor posture, stress, jaw clenching, and eye strain, while migraines often involve hormonal shifts, specific foods, and sensory stimuli.
- Red flags such as sudden severe pain, neurological symptoms, fever with neck stiffness, or headache after head injury demand urgent medical evaluation.
- Preventive measures like consistent sleep, hydration, and trigger tracking help reduce chronic headache frequency, with some cases needing specialized neck treatment or medication.
The fastest way to sort one from the other is to ask three questions: Where does it hurt? How strong is it? Does anything else come with it? Your answers usually point you in the right direction before you even open a symptom checklist.
Tension-type headaches produce a steady, pressing pain, often described as a headband tightening around the skull. It sits on both sides, stays mild to moderate, and generally doesn’t get worse when you climb stairs or go for a walk, according to Mayo Clinic. Migraines behave differently. The pain is often one-sided, throbs or pulses rather than presses, and climbs to moderate or severe intensity. Physical activity tends to make a migraine worse, not better, which is itself a useful clue during an attack, per WebMD.
| Feature | Tension headache | Migraine |
|---|---|---|
| Pain quality | Pressing, tightening, bandlike | Throbbing, pulsating |
| Typical location | Bilateral (both sides) | Often unilateral (one side) |
| Duration | several hours to several days | 4 to 48 hours untreated |
| Associated symptoms | Rarely nausea; mild light or sound sensitivity possible | Nausea, vomiting, strong light and sound sensitivity, sometimes aura |
| Worsening with activity | Usually no | Usually yes |
| Usual first-line treatments | Acetaminophen, NSAIDs, stress and posture management | NSAIDs or triptans, dark quiet rest, antiemetics if needed |
Not every headache fits neatly into one box. A few patterns worth knowing:
Pro Tip: Keep a simple headache diary for four weeks. Note the time it started, what you were doing, pain location and intensity on a 1 to 10 scale, and any nausea or light sensitivity. Four weeks of data does more to clarify your headache type than a single bad day ever will, and it gives your doctor something concrete to work from, a pattern WebMD recommends for anyone trying to nail down their trigger pattern.
The two headache types often share a few triggers but diverge on others, and knowing which is which helps you target the right fix instead of guessing.
Migraine triggers tend to be more specific and more individual. Hormonal shifts, particularly around menstrual cycles, are a well-documented driver. Certain foods (aged cheese, processed meats, alcohol, especially red wine) show up repeatedly in patient reports. Bright or flickering light, strong smells, and sudden weather changes round out the list. Tension headache causes lean more mechanical and behavioral: prolonged stress, poor posture at a desk, clenched jaw muscles, and eye strain from screen time are the usual suspects.
Some triggers don’t discriminate. Both headache types respond to:
There’s a third category worth knowing about: cervicogenic headache. This type originates in the neck, typically from joint dysfunction or muscle tightness in the upper cervical spine, and refers pain up into the head. It can mimic a tension headache closely, but the giveaway is that it’s often reproducible by moving or pressing on the neck. Harvard Health notes this pattern is common enough that it’s worth ruling in or out before assuming a headache is purely tension-type.
Most headaches don’t require a trip to the emergency room, but clinicians use a specific process to sort out the ones that do. A typical workup starts with a detailed history (when it started, how it’s changed, what makes it better or worse), a neurologic exam checking reflexes, coordination, and vision, and bloodwork or imaging only when something in that history raises a flag. Most tension headaches and typical migraines don’t need a CT scan or MRI at all.
Certain symptoms change that calculation immediately. Seek urgent evaluation if you experience:
For anything outside that list, your primary care provider is the right first stop. They can manage most tension headaches and uncomplicated migraines directly. A neurology referral usually comes into play when headaches are frequent, resistant to standard treatment, or accompanied by neurologic symptoms that need closer investigation. Anything on the red-flag list above belongs in an emergency department, not a scheduled appointment.
Treatment splits along the same lines as diagnosis: what works well for tension-type pain isn’t always the right tool for a migraine, and using the wrong one repeatedly can create a second problem on top of the first.
For tension headaches, over-the-counter options like acetaminophen and NSAIDs (ibuprofen, naproxen) are usually effective as first-line treatment. The catch is frequency. Using simple analgesics more than two to three days a week raises the risk of medication-overuse headache, a rebound cycle where the treatment itself starts perpetuating the pain, according to Mayo Clinic’s treatment guidance.
Migraines often need a different toolkit. Triptans are prescription medications designed specifically to interrupt migraine attacks by acting on blood vessels and pain pathways in the brain, and they work best taken early in an attack rather than after pain has fully set in. Antiemetics address the nausea that frequently accompanies migraine and can be paired with other treatments. Neither is something to self-prescribe. If OTC options aren’t cutting it, that’s the conversation to have with a prescriber, not a reason to double up on ibuprofen.
Non-drug approaches matter for both headache types and often get underused:
Pro Tip: Cap simple analgesic use at two to three days a week. If you’re reaching for painkillers more often than that, it’s a signal to talk to a doctor about prevention rather than just treating each attack as it comes, a threshold Mayo Clinic specifically calls out as a driver of medication-overuse headache.
Prevention starts with the basics, and it’s worth taking them seriously rather than treating them as an afterthought to medication. Consistent sleep and wake times, steady hydration, regular exercise, and stable caffeine intake all reduce headache frequency for many people. Tracking triggers in that four-week diary mentioned earlier turns vague suspicion (“I think it’s stress”) into something you can actually act on.

When migraines happen frequently enough, roughly four or more days a month per guidance summarized by NICE, daily preventive medication becomes worth discussing with a prescriber. These preventive classes work differently from abortive treatments taken during an attack; they aim to lower frequency and severity over time rather than stop a single episode.
Some people end up with what’s sometimes called a transformed or chronic headache, where frequent migraine attacks blend into near-constant background tension-type pain. This overlap makes headaches harder to classify and treat with a single approach, and it’s usually where multidisciplinary care, combining medical management with physical therapy or targeted manual therapy, produces better results than medication alone.
If your headache tends to start at the base of your skull, worsens with certain neck movements, or comes with noticeable tenderness when you press along your upper spine, the neck may be playing a bigger role than you think. This pattern shows up often enough that some estimates put cervicogenic origins behind a meaningful share of chronic headache presentations, and those cases tend to respond better to hands-on treatment than to painkillers alone.
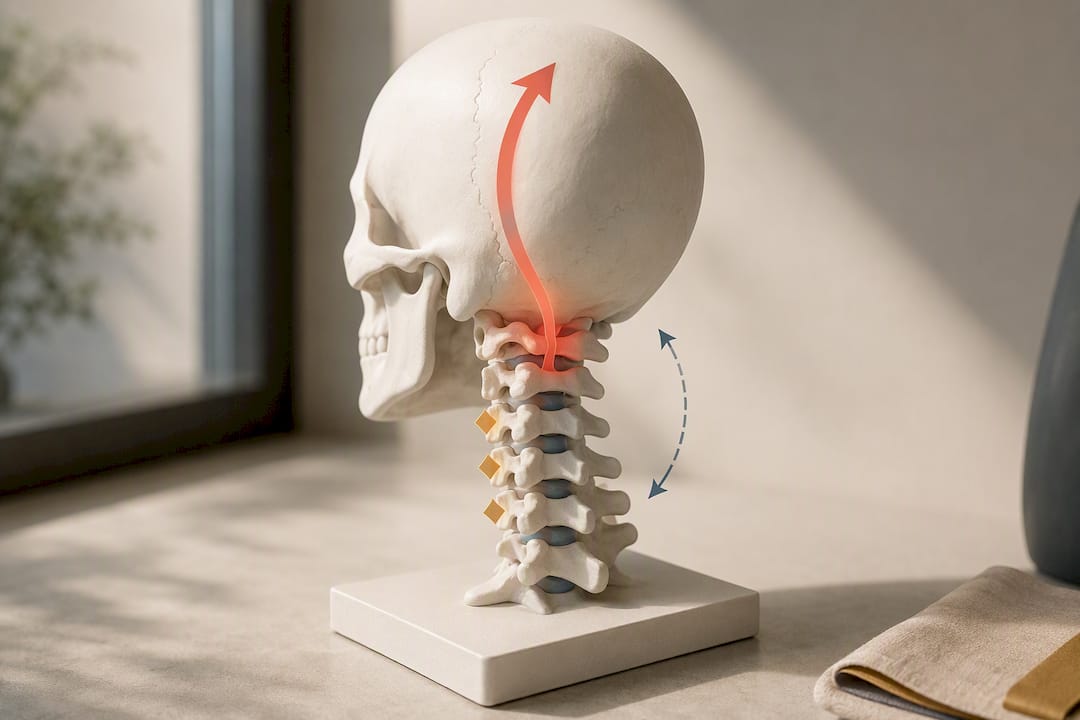
At Shephardhealth, several non-invasive approaches address this specifically. Massage therapy and Active Release Technique both target the muscle tightness that refers pain into the head, while Graston Technique works on stubborn soft-tissue restrictions that manual pressure alone doesn’t reach. Spinal decompression and laser therapy come into play for cases where nerve irritation or disc-related pressure in the cervical spine is a contributing factor.
A few things matter for safety here. High-velocity neck manipulations aren’t appropriate for everyone, and providers should screen for vascular risk factors before performing them, given the rare but serious risk of arterial injury in susceptible patients. And none of this replaces medical evaluation. If your headache carries any of the red flags covered earlier, sudden severe onset, neurologic symptoms, fever with neck stiffness, that needs a medical workup first, not a massage table.
Three quick rules cut through most of the guesswork. Mild, bilateral, pressing pain without nausea: treat at home and monitor. Moderate to severe, one-sided, throbbing pain with nausea or light sensitivity: schedule time with your primary care provider. Anything matching a red flag, sudden severe onset, neurologic symptoms, fever with stiff neck: go to the emergency department, don’t wait it out.
Before any non-urgent appointment, spend four weeks on that headache diary unless red flags are present. Bring your current medication list, the diary itself, and specific examples of your worst recent attacks. That combination gives a clinician far more to work with than “I get headaches sometimes.”
— Deane
If your headaches trace back to neck tension, poor posture, or muscle tightness across your shoulders, that’s exactly the kind of pain clinical teams in healthcare settings typically address, and timely appointments help you avoid long waits while your headaches persist.
Chiropractic care and physical rehabilitation focus on the biomechanical side of headaches: tight cervical muscles, restricted joint movement, and posture patterns that keep reproducing pain even after the medication wears off. Services like Active Release Technique and massage therapy work directly on the soft tissue contributing to tension-type and cervicogenic headaches, while a full assessment helps determine whether your neck mechanics are actually part of the problem. This kind of care works alongside your doctor’s migraine management, not instead of it. If you suspect your neck is feeding your headaches, book an assessment through Shephardhealth’s services page and get a clear picture of what’s driving your pain.
For deeper detail beyond this guide, a few sources stand out: Mayo Clinic for symptom and treatment breakdowns, WebMD for side-by-side trigger comparisons, Harvard Health for neck-origin headache detail, NICE for clinical frequency guidelines, and the WHO for global headache burden data.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Check three things: location, intensity, and associated symptoms. Bilateral, mild to moderate, pressing pain with no nausea points to tension headache, while one-sided, throbbing, moderate to severe pain with nausea or light sensitivity points to migraine. A four-week headache diary makes the pattern much clearer if you’re still unsure.
This isn’t a recognized clinical framework from the sources covered here, and definitions of it vary widely online. Rather than repeat an unverified rule, the more reliable approach is tracking your specific triggers and symptoms in a headache diary and discussing patterns with your doctor.
Stress, poor posture, jaw clenching, and eye strain from extended screen time are the most common tension headache causes. Shared triggers with migraine include poor sleep, dehydration, skipped meals, and sudden changes in caffeine intake.
Over-the-counter acetaminophen or NSAIDs work for most acute episodes, but limiting use to two to three days a week avoids medication-overuse headache. Heat application, neck stretches, and massage therapy targeting shoulder and neck tension also provide relief, especially for headaches with a clear muscular component.
Yes. Cervicogenic headaches originate in the neck and often mimic tension-type pain closely, though they’re typically reproducible by pressing on or moving the neck. Physical therapy and targeted manual therapy tend to work better for these cases than analgesics alone.
Same Day Appointments Available
We Direct Bill!