

Shockwave therapy (extracorporeal shockwave therapy, or ESWT) is one of the better-studied non-surgical options for calcific tendonitis, especially in the shoulder. Focused, high-energy sessions have the strongest evidence. Results depend on the device, the energy level, the stage of your calcium deposit and what you do alongside the sessions. This guide explains how it works, what the research supports, who should not have it, and how to judge a clinic’s plan. It also covers the common follow-up question about hip bursitis.
Calcific tendonitis (also written calcific tendinitis or calcific tendinopathy) happens when calcium deposits form within a tendon. The shoulder’s rotator cuff, particularly the supraspinatus tendon, is the classic site. The pain can be severe and often worsens at night or when you lift your arm. Some people lose a good deal of shoulder motion.
The condition tends to move through stages. A deposit can sit quietly for a while, then become irritated as the body tries to clear it. A 2025 review of treatment options notes that decisions depend on the stage of the deposit, prognostic factors, previous failed treatments, pain level and functional disability. That is why two people with the same X-ray finding can need different plans.
The same review points out that calcific tendonitis often resolves spontaneously. For that reason the most advisable approach is to use conservative care first, such as education, reassurance and targeted physiotherapy. Shockwave is best seen as a strong adjunct in a patient-centered plan.
A shockwave device delivers short, high-pressure acoustic pulses through the skin into the painful tendon. In calcific tendonitis the aim is twofold. The mechanical energy is thought to help fragment the crystalline deposit, and it stimulates a healing response in the surrounding tissue. Most patients describe the treatment as intense but brief, a rhythmic tapping that can be uncomfortable over a tender spot.
Treatment is non-invasive. There is no needle, no incision and no anesthetic in a typical session. Your clinician finds the painful area with you, applies gel, and adjusts energy to what you can tolerate while still delivering a useful dose. If you want a walk-through of a session from start to finish, our page on the shockwave therapy pain procedure covers it step by step.
Practitioners often say the term “shockwave” is an umbrella. The devices behind it differ in physics, depth and energy, and outcomes can vary with the choice of device, energy level and number of sessions, as clinicians writing in SICOT-J emphasize.
| Feature | Focused shockwave | Radial pressure wave |
|---|---|---|
| How energy is delivered | Concentrated at a defined depth in the tissue | Spreads out from the applicator, strongest at the surface |
| Energy range | Low to high | Generally low to medium |
| Evidence for calcific deposits | Stronger, particularly at high energy | Limited and contradictory |
| Typical use | Deeper or more specific targets, such as a deposit in the rotator cuff | Broader, more superficial soft tissue complaints |
The review of therapeutic options describes this stronger recommendation for focused waves in calcific deposits and the weaker, inconsistent data for radial waves. An international Delphi study on shockwave in sports medicine likewise asks clinicians to distinguish focused from radial waves and their energy levels (low, medium, high). So a fair question at your first visit is: which type of device will you use on my shoulder, and why?
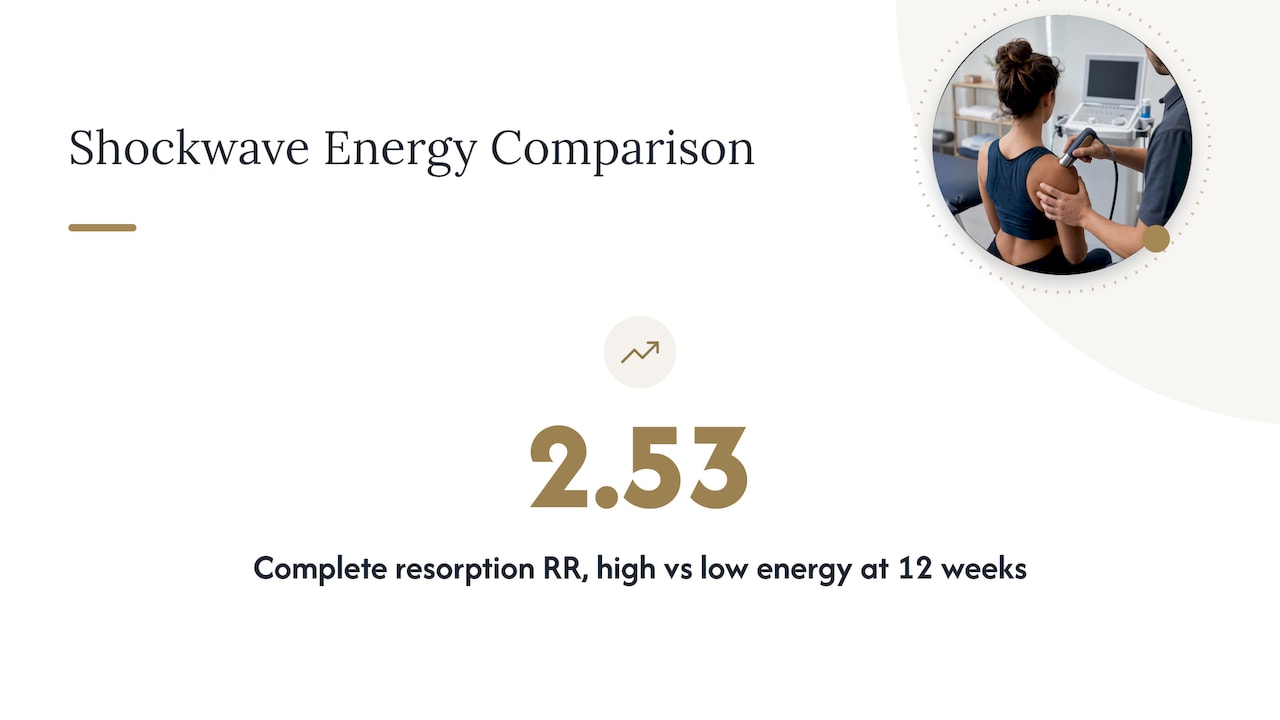
The strongest evidence is for the rotator cuff. A systematic review with meta-analysis found ESWT effective for calcific tendinopathy of the rotator cuff. In that analysis, high-energy shockwave produced significantly higher complete resorption of the calcification at 12 weeks than low-energy shockwave (risk ratio 2.53).
An earlier Annals of Internal Medicine review looked at high-energy ESWT for chronic calcific tendinitis of the shoulder, and its conclusions pointed the same way: high energy matters.
Two honest caveats apply. Many trials are small, and results vary between people. Resorption of the deposit on imaging and relief of your pain do not always line up. Some people feel much better while a trace of calcium remains. Others see the deposit shrink but still need rehab to regain motion and strength.
Shockwave is not the only option for a stubborn deposit. Ultrasound-guided needle lavage (barbotage) is another, and there is a meta-analysis comparing ESWT with lavage for pain in rotator cuff calcific tendinopathy. Which one suits you depends on the stage of the deposit, your pain and what you have already tried. That decision belongs with your physician or a shoulder specialist, and a clinic that offers shockwave should be willing to say when another route makes more sense for you.
Many people searching this topic also ask about hip bursitis. The evidence there is thinner than for calcific shoulder deposits. A 2025 systematic review of tendinopathies around the hip and pelvis covered proximal hamstring tendinopathy, gluteal tendinopathy (greater trochanteric pain syndrome) and calcific tendinopathy. It found significant improvement in pain and function with ESWT, with an overall adverse event rate of 12%.
For trochanteric bursitis specifically, a health technology assessment found low-to-moderate quality evidence that ESWT helps compared with minimal or no treatment. Compared with another active treatment, it generally showed no significant difference. In practice, “hip bursitis” pain is often really a gluteal tendon problem. Shockwave may be one tool within a plan that also addresses load, strength and mechanics. It is not a guaranteed fix for bursitis, and no honest clinic should promise it is.
Shockwave can reduce pain and help the tendon respond. It does not correct why the shoulder became overloaded. A recent clinical commentary describes shockwave as most successful when integrated into a broader rehabilitation protocol. For active people, pairing it with a personalized exercise program tends to support better long-term function than shockwave alone, because the program addresses the biomechanical issues behind the problem.
For the shoulder, that usually means looking at:
If you want to see how we structure early shoulder work, read our guide to rotator cuff rehab exercises and our overview of rotator cuff tendinopathy treatment.
Shockwave is not for everyone. The 2025 international Delphi study reached more than 95% agreement that active malignancy near the treatment area is an absolute contraindication for both focused and radial shockwave. The ISMST guidelines list contraindications for high-energy focused sources that include these:
Clinical practice also treats a pacemaker or other implanted electrical device in the treatment area, and active infection at the site, as reasons to hold off. Tell your clinician about any of these, any blood thinners, and your full medical history before the first session.
Recent steroid injection. Many practitioners recommend waiting at least six weeks after a local corticosteroid injection before shockwave, as noted in the Delphi study. Ask any provider what their wait-time protocol is. If you have had an injection recently, give your clinic the date.
See your family physician promptly, before any manual or shockwave treatment, if your shoulder pain follows a significant fall or trauma, comes with fever, or is accompanied by chest pain or arm numbness. Those need medical assessment first.
Shockwave is non-invasive, but it is not sensation-free. The ISMST guidelines describe side effects after treatment that include temporary increases in pain, skin reddening, bruising and mild swelling. Some sensitive patients have reported transient tinnitus. These reactions are usually short-lived. Severe or prolonged discomfort should be reported to your provider, and ringing in the ears that does not settle quickly should be checked.
You will usually be asked to avoid aggravating the shoulder hard for a short period, then to resume graded movement. Your clinician should tell you exactly what that looks like for your sport or job, because the answer differs for a swimmer, a tradesperson and someone who sits at a desk.
We see calcific tendonitis as a problem to be assessed, not a diagnosis to be treated with one device. When someone comes in with a painful shoulder, we begin with a thorough biomechanical assessment, review any imaging they have, and ask what they need to get back to. The research supports shockwave for calcific deposits in the rotator cuff, but it also tells us that most people do best when it is paired with active rehabilitation.
That is why our plans combine technologies with hands-on care and exercise. Shockwave may sit alongside Active Release Technique, laser therapy or Graston Technique, depending on what we find. We would rather tell you honestly when a deposit is likely to settle with conservative care, or when you should see your physician about injections or a procedure, than sell you a course of sessions you do not need.
— Deane
Whether you choose us or someone else, these criteria help you compare providers on substance.
Our Calgary clinic offers shockwave therapy as part of a broader plan that can include chiropractic care and physical rehabilitation. We offer same-day appointments and direct insurance billing where applicable. Your first visit centers on your history, a biomechanical assessment and a conversation about your goals, so you leave knowing what we think is going on and what comes next. You can read more about what to expect on a first chiropractic visit, or start from our main site to book.
If your problem is elsewhere, our pages on shockwave for knee pain and Achilles tendinopathy explain how the approach adapts.
In trials, high-energy focused shockwave has been linked to higher rates of complete resorption of rotator cuff calcifications than low-energy treatment. Resorption can take weeks to months, and not every deposit disappears. Pain relief and function are the outcomes that matter most to you.
Yes. Education, reassurance and targeted physiotherapy are the usual first steps, and many deposits settle with them. Exercise also remains important alongside shockwave, because it addresses strength and mechanics that contributed to the problem.
The evidence is less robust than for calcific shoulder tendinopathy. Reviews show benefit for gluteal and other hip tendinopathies, and some low-to-moderate quality evidence for trochanteric bursitis compared with no treatment. It is usually one part of a broader plan that includes strengthening and load management.
Avoid it with a malignant tumor in the treatment area, a pacemaker or electrical implant in the area, pregnancy when the fetus would be in the field, or an active infection at the site. A significant coagulation disorder is also a listed contraindication for high-energy focused treatment. Tell your clinician about recent corticosteroid injections, because many wait at least six weeks.
It varies with the device, energy level and the deposit itself, so no single number fits everyone. Your clinician should set out an expected number of sessions at the start and review progress along the way.
Same Day Appointments Available
We Direct Bill!